Dernière mise à jour: Août 17, 2026
Enfant prématuré, consultation gratuite
Naissance prématurée
Autres noms Naissance prématurée, prématurés, les prématurés
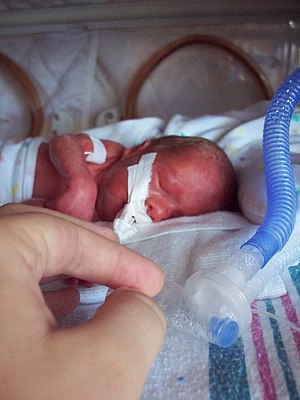
Nourrisson prématuré avec ventilateur.jpg
Bébé prématuré intubé dans un incubateur
Néonatalogie spécialisée, Pédiatrie, Obstétrique
Symptômes Naissance d'un bébé à moins de 37 semaines’ âge gestationnel[1]
Complications Paralysie cérébrale, retards de développement, problèmes d'audition, problèmes de vue[1]
Causes Souvent inconnues[2]
Facteurs de risque Diabète, hypertension artérielle, Gestation multiple, obésité ou insuffisance pondérale, un certain nombre d'infections vaginales, maladie coeliaque, fumer du tabac, stress psychologique[2][3][4]
Progestérone préventive[5]
Traitement Corticostéroïdes, garder le bébé au chaud grâce au contact peau à peau, soutenir l'allaitement, traiter les infections, soutenir la respiration[2][6]
Fréquence ~15 millions par an (12% de livraisons)[2]
Décès 805,800[7]
Naissance prématurée, également connu sous le nom de naissance prématurée, la naissance d'un bébé est-elle à moins de 37 semaines d'âge gestationnel, par opposition à un accouchement à terme à environ 40 semaines.[1] L'accouchement prématuré très précoce a lieu avant 32 semaines, un accouchement prématuré survient entre 32 et 36 semaines, l'accouchement peu prématuré se situe entre 34 et 36 semaines’ gestation.[8] Ces bébés sont également connus sous le nom de bébés prématurés ou familièrement prématurés. (Anglais américain)[9] ou les prématurés (Anglais australien).[10] Les symptômes du travail prématuré comprennent des contractions utérines qui surviennent plus souvent que toutes les dix minutes et/ou une fuite de liquide du vagin avant 37 semaines.[11] Les nourrissons prématurés courent un plus grand risque de paralysie cérébrale, retards de développement, des problèmes d’audition et des problèmes de vision.[1] Plus un bébé naît tôt, plus ces risques seront grands.[1]
La cause de l’accouchement prématuré spontané est souvent inconnue.[2] Les facteurs de risque incluent le diabète, hypertension artérielle, gestation multiple (être enceinte de plus d'un bébé), être obèse ou avoir un poids insuffisant, infections vaginales, exposition à la pollution atmosphérique, fumer du tabac, et le stress psychologique.[2][3][12] Pour une grossesse en santé, le déclenchement médical du travail ou la césarienne ne sont pas recommandés avant 39 semaines, sauf si cela est nécessaire pour d'autres raisons médicales.[2] Il peut y avoir certaines raisons médicales pour un accouchement précoce, comme la prééclampsie.[13]
L'accouchement prématuré peut être évité chez les personnes à risque si l'hormone progestérone est prise pendant la grossesse.[5] Les preuves ne soutiennent pas l’utilité du repos au lit.[5][14] On estime qu'au moins 75% des nourrissons prématurés survivraient avec un traitement approprié, et le taux de survie est le plus élevé parmi les nourrissons nés le plus tard en gestation.[2] Chez les femmes qui pourraient accoucher entre 24 et 37 semaines, le traitement aux corticostéroïdes peut améliorer les résultats.[6][15] Un certain nombre de médicaments, y compris la nifédipine, peut retarder l'accouchement afin que la mère puisse être transférée là où davantage de soins médicaux sont disponibles et où les corticostéroïdes ont plus de chances d'agir.[16] Une fois le bébé né, les soins comprennent le maintien du bébé au chaud par contact peau à peau ou par incubation, soutenir l’allaitement maternel et/ou l’alimentation artificielle, traiter les infections, et soutenir la respiration.[2] Les bébés prématurés nécessitent parfois une intubation.[2]
La naissance prématurée est la cause de décès la plus fréquente chez les nourrissons dans le monde.[1] À propos 15 millions de bébés sont prématurés chaque année (5% à 18% de toutes les livraisons).[2] Les naissances peu prématurées représentent 75% de toutes les naissances prématurées.[17] Ce taux est incohérent selon les pays. Au Royaume-Uni 7.9% des bébés naissent prématurément et aux États-Unis 12.3% de toutes les naissances ont lieu avant 37 semaines de gestation.[18][19] Environ 0.5% des naissances sont des naissances périviables extrêmement précoces (20-25 semaines de gestation), et ceux-ci représentent la plupart des décès.[20] Dans de nombreux pays, les taux de naissances prématurées ont augmenté entre les années 1990 et 2010.[2] Les complications liées aux naissances prématurées ont entraîné 0.81 millions de morts en 2015, vers le bas de 1.57 millions en 1990.[7][21] La chance de survie à 22 les semaines, c'est environ 6%, alors qu'à 23 semaines c'est 26%, 24 semaines 55% et 25 semaines environ 72%.[22] Les chances de survie sans difficultés à long terme sont moindres.[23
Signes et symptômes
Une nouvelle mère tient son bébé prématuré dans ses bras à l'USIN du centre médical Kapiolani à Honolulu, Hawaii
Les signes et symptômes du travail prématuré comprennent quatre contractions utérines ou plus en une heure. Contrairement au faux travail, le vrai travail s'accompagne d'une dilatation et d'un effacement du col. Aussi, saignements vaginaux au troisième trimestre, forte pression dans le bassin, ou des douleurs abdominales ou dorsales pourraient être des indicateurs d'un accouchement prématuré sur le point de se produire.. Un écoulement aqueux du vagin peut indiquer une rupture prématurée des membranes qui entourent le bébé.. Bien que la rupture des membranes puisse ne pas être suivie de travail, généralement, l'accouchement est indiqué comme une infection (chorioamnionite) est une menace sérieuse pour le fœtus et la mère. Dans certains cas, le col se dilate prématurément sans douleur ni contractions perçues, afin que la mère ne présente des signes avant-coureurs que très tard dans le processus d'accouchement.
Causes
Les principales catégories de causes d’accouchement prématuré sont le déclenchement du travail prématuré et le travail prématuré spontané..
Facteurs de risque
La cause exacte de l’accouchement prématuré spontané est difficile à déterminer et elle peut être causée par de nombreux facteurs différents, alors que le travail est un processus complexe.[24][25] Quatre voies différentes ont été identifiées pouvant entraîner une naissance prématurée et disposent de preuves considérables: activation endocrinienne fœtale précoce, distension utérine (décollement placentaire), saignement décidal, et inflammation ou infection intra-utérine.[26]
L'identification précoce des femmes présentant un risque élevé d'accouchement permettrait aux services de santé de prodiguer des soins spécialisés à ces femmes et à leurs bébés., par exemple un hôpital doté d'une unité de soins spéciaux pour bébés telle qu'une unité de soins intensifs néonatals (USIN). Dans certains cas, il est peut-être possible de retarder l'accouchement. Des systèmes de notation des risques ont été suggérés comme approche pour identifier les personnes présentant un risque plus élevé., cependant, Il n'existe pas de recherches approfondies dans ce domaine, de sorte qu'il n'est pas clair si l'utilisation de systèmes de notation des risques pour identifier les mères prolongerait la grossesse et réduirait ou non le nombre de naissances prématurées.[27]
Facteurs maternels
Facteur de risque Risque relatif[28] 95% confiance
intervalle[28]
Fibronectine fœtale 4.0 2.9–5,5
Longueur cervicale courte 2.9 2.1–3,9
Chlamydia 2.2 1.0–4,8
Faible statut socio-économique 1.9 1.7–2.2
Gain de poids important ou faible pendant la grossesse 1.8 1.5–2.3
Petite taille maternelle 1.8 1.3–2,5
Parodontite 1.6 1.1–2.3
Maladie coeliaque 1.4[29] 1.2–1,6[29]
Bactériurie asymptomatique 1.1 0.8–1,5
IMC élevé ou faible 0.96 0.66–1,4
rapport de cotes
Antécédents d'accouchement prématuré spontané 3.6 3.2–4.0
Vaginose bactérienne 2.2 1.5–3.1
Ethnie/race noire 2.0 1.8–2.2
Ascendance philippine[30] 1.7 1.5–2.1
Grossesse non désirée[31]:1 1.5 1.41-1.61
Grossesse non désirée[31]:1 1.31 1.09-1.58
Etre célibataire/célibataire[32] 1.2 1.03–1,28
Pourcentage de naissances prématurées en Angleterre et au Pays de Galles 2011, selon l'âge de la mère et selon qu'il s'agisse d'une naissance unique ou multiple.
Des facteurs de risque ont été identifiés chez la mère, liés à un risque plus élevé d'accouchement prématuré.. Ceux-ci incluent l'âge,[33] indice de masse corporelle élevé ou faible (IMC),[34][35] délai entre les grossesses,[36] précédent spontané (c'est-à-dire, fausse-couche) ou avortements chirurgicaux,[37][38] grossesses non désirées,[31] maladie cœliaque non traitée ou non diagnostiquée,[29][4] difficultés de fertilité, exposition à la chaleur,[39] et les variables génétiques.[40]
Les études sur le type de travail et l’activité physique ont donné des résultats contradictoires, mais il est d'avis que les conditions stressantes, travaux forcés, et les longues heures de travail sont probablement liées à l'accouchement prématuré.[33] L'obésité ne conduit pas directement à une naissance prématurée;[41] cependant, elle est associée au diabète et à l'hypertension qui sont en soi des facteurs de risque.[33] Dans une certaine mesure, ces personnes peuvent avoir des conditions sous-jacentes (c'est-à-dire, malformation utérine, hypertension, diabète) qui persistent. Les couples qui ont essayé plus de 1 année par rapport à ceux qui ont essayé moins de 1 un an avant de parvenir à une conception spontanée ont un rapport de cotes ajusté de 1.35 (95% intervalle de confiance 1.22-1.50) de naissance prématurée.[42] Les grossesses après FIV présentent un plus grand risque d'accouchement prématuré que les conceptions spontanées après plus de 1 année d'essai, avec un rapport de cotes ajusté de 1.55 (95% CI 1.30-1.85).[42]
Certaines ethnies peuvent également présenter un risque plus élevé. Par exemple, aux États-Unis. et le Royaume-Uni, Les femmes noires ont des taux de naissance prématurée de 15 à 18 %, plus du double de celui de la population blanche. De nombreuses femmes noires ont des taux de naissance prématurée plus élevés en raison de plusieurs facteurs, mais le plus courant est un stress chronique élevé., ce qui peut éventuellement conduire à une naissance prématurée.[43] Adult chronic disease isn’t always the case with premature birth in Black women, ce qui rend le principal facteur de naissance prématurée difficile à identifier.[43] Les Philippins courent également un risque élevé d’accouchement prématuré, et on estime que près de 11 à 15 % des Philippins nés aux États-Unis. (par rapport aux autres Asiatiques de 7.6% et les blancs à 7.8%) sont prématurés.[44] Les Philippins constituent un facteur de risque important, comme en témoigne le fait que les Philippines occupent le huitième rang mondial pour les naissances prématurées., le seul pays non africain dans le top 10.[45] Cet écart n’est pas visible par rapport aux autres groupes asiatiques ou aux immigrants hispaniques et reste inexpliqué.[33] La constitution génétique est un facteur de causalité dans l’accouchement prématuré. La génétique est un facteur important expliquant pourquoi les Philippins présentent un risque élevé de naissance prématurée, car les Philippins ont une forte prévalence de mutations qui les prédisposent aux naissances prématurées.[44] Un intra- et une augmentation transgénérationnelle du risque d’accouchement prématuré a été démontrée.[40] Aucun gène n’a été identifié.
L'état matrimonial est associé au risque d'accouchement prématuré. Une étude de 25,373 les grossesses en Finlande ont révélé que les mères célibataires avaient plus d'accouchements prématurés que les mères mariées (P = 0,001).[32] La grossesse hors mariage était globalement associée à un 20% augmentation du total des effets indésirables, même à une époque où la Finlande offrait des soins de maternité gratuits. Une étude au Québec sur 720,586 naissances de 1990 à 1997 ont révélé un risque moindre de naissance prématurée pour les nourrissons dont la mère est légalement mariée que pour ceux dont les parents sont mariés ou non.[46][a besoin d'une mise à jour]
Facteurs pendant la grossesse
Médicaments pendant la grossesse, conditions de vie, pollution de l'air, fumeur, drogues illicites ou alcool, infection, ou un traumatisme physique peut également provoquer un accouchement prématuré.
Pollution atmosphérique: Vivre dans une zone avec une forte concentration de pollution atmosphérique est un facteur de risque majeur de travail prématuré, y compris vivre à proximité de routes principales ou d'autoroutes où les émissions des véhicules sont élevées en raison des embouteillages ou qui constituent un itinéraire pour les camions diesel qui ont tendance à émettre plus de pollution.[47][48][12] Les pays où la pollution atmosphérique associée aux naissances prématurées est la plus élevée se trouvent en Asie du Sud et de l’Est., le Moyen-Orient, Afrique du Nord, et l’Afrique subsaharienne occidentale.[citation nécessaire]
L'utilisation de médicaments contre la fertilité qui stimulent l'ovaire à libérer plusieurs ovules et de la FIV avec transfert d'embryons multiples a été impliquée comme facteur de risque d'accouchement prématuré.. Le travail doit souvent être déclenché pour des raisons médicales; ces conditions incluent l'hypertension artérielle,[49] pré-éclampsie,[50] diabète maternel,[51] asthme, maladie de la thyroïde, et les maladies cardiaques.
Certaines conditions médicales chez la mère enceinte peuvent également augmenter le risque d'accouchement prématuré.. Certaines femmes ont des problèmes anatomiques qui empêchent de porter leur bébé à terme.. Ceux-ci incluent un col faible ou court (le prédicteur le plus puissant d’une naissance prématurée).[52][53][54][49] Les femmes ayant des saignements vaginaux pendant la grossesse courent un risque plus élevé d’accouchement prématuré. Bien que les saignements au cours du troisième trimestre puissent être un signe de placenta prævia ou de décollement placentaire – des affections qui surviennent fréquemment avant terme –, même des saignements plus précoces qui ne sont pas causés par ces affections sont liés à un taux de naissances prématurées plus élevé.[55] Femmes ayant des quantités anormales de liquide amniotique, si c'est trop (hydramnios) ou trop peu (oligohydramnios), sont également en danger.[33] L'anxiété et la dépression ont été associées comme facteurs de risque d'accouchement prématuré.[33][56]
L'usage du tabac, cocaïne, et un excès d'alcool pendant la grossesse augmente le risque d'accouchement prématuré. Le tabac est la drogue la plus couramment utilisée pendant la grossesse et contribue de manière significative à l'accouchement avec un faible poids à la naissance.[57] Les bébés présentant des malformations congénitales courent un risque plus élevé de naître prématurément.[58]
Le tabagisme passif et/ou le tabagisme avant la grossesse influencent la probabilité d'un accouchement prématuré. L'Organisation mondiale de la santé a publié une étude internationale en mars 2014.[59]
La présence d'anticorps anti-thyroïdiens est associée à un risque accru d'accouchement prématuré avec un rapport de cotes de 1.9 et 95% intervalle de confiance de 1,1 à 3,5.[60]
La violence intime contre la mère est un autre facteur de risque d'accouchement prématuré.[61]
Un traumatisme physique peut entraîner une naissance prématurée. Il a été démontré que la méthode culturelle nigériane du massage abdominal entraîne 19% naissance prématurée chez les femmes au Nigéria, ainsi que de nombreux autres effets indésirables pour la mère et le bébé.[62] Massothérapie effectuée par un massothérapeute certifié/agréé ou formé. Cela ne doit pas être confondu avec le massage effectué par un massothérapeute entièrement formé et agréé ou par d'autres personnes importantes formées pour fournir des massages pendant la grossesse., qui s'est avéré avoir de nombreux résultats positifs pendant la grossesse, y compris la réduction des naissances prématurées, moins de dépression, cortisol inférieur, et une réduction de l'anxiété.[63]
Infection
La fréquence d’infection lors d’un accouchement prématuré est inversement proportionnelle à l’âge gestationnel. L’infection à Mycoplasma genitalium est associée à un risque accru d’accouchement prématuré, et avortement spontané.[64]
Les micro-organismes infectieux peuvent être ascendants, hématogène, iatrogène par une procédure, ou rétrograde par les trompes de Fallope. Depuis les caduques, elles peuvent atteindre l'espace entre l'amnios et le chorion., le liquide amniotique, et le fœtus. Une chorioamnionite peut également entraîner une septicémie chez la mère.. L'infection fœtale est liée à une naissance prématurée et à un handicap important à long terme, notamment la paralysie cérébrale.[65]
Il a été rapporté qu'une colonisation asymptomatique de la caduque se produit jusqu'à 70% de femmes à terme utilisant une sonde ADN, ce qui suggère que la présence d'un micro-organisme à elle seule pourrait être insuffisante pour déclencher la réponse infectieuse.
Comme cette maladie est plus répandue chez les femmes noires aux États-Unis. et le Royaume-Uni, cela a été suggéré comme explication du taux plus élevé de naissances prématurées dans ces populations. Il est d'avis que la vaginose bactérienne avant ou pendant la grossesse peut affecter la réponse inflammatoire déciduale qui conduit à un accouchement prématuré.. La maladie connue sous le nom de vaginite aérobie peut être un facteur de risque sérieux de travail prématuré.; plusieurs études antérieures n'ont pas réussi à reconnaître la différence entre la vaginite aérobie et la vaginose bactérienne, ce qui peut expliquer une partie de la contradiction dans les résultats.[66]
Les infections à levures non traitées sont associées à un accouchement prématuré.[67]
Une revue des antibiotiques prophylactiques (administré pour prévenir l’infection) aux deuxième et troisième trimestres de la grossesse (13–42 semaines de grossesse) constaté une réduction du nombre de naissances prématurées chez les femmes atteintes de vaginose bactérienne. Ces antibiotiques ont également réduit le nombre de pertes des eaux avant le travail lors des grossesses à terme., réduit le risque d’infection de la muqueuse utérine après l’accouchement (endométrite), et taux d'infection gonococcique. Cependant, the women without bacterial vaginosis did not have any reduction in preterm births or pre-labor preterm waters breaking. Much of the research included in this review lost participants during follow-up so did not report the long-term effects of the antibiotics on mothers or babies. More research in this area is needed to find the full effects of giving antibiotics throughout the second and third trimesters of pregnancy.[68]
A number of maternal bacterial infections are associated with preterm birth including pyelonephritis, asymptomatic bacteriuria, pneumonie, and appendicitis. A review into giving antibiotics in pregnancy for asymptomatic bacteriuria (urine infection with no symptoms) a constaté que la recherche était de très mauvaise qualité mais qu'elle suggérait que la prise d'antibiotiques réduisait le nombre de naissances prématurées et de bébés de faible poids à la naissance.[69] Une autre revue a révélé qu'une dose d'antibiotiques ne semblait pas aussi efficace qu'une cure d'antibiotiques, mais que moins de femmes signalaient des effets secondaires suite à une seule dose.[70] Cette revue recommande que des recherches supplémentaires soient nécessaires pour découvrir la meilleure façon de traiter la bactériurie asymptomatique.[69]
Une étude différente a révélé que les naissances prématurées se produisaient moins chez les femmes enceintes qui subissaient des tests de routine pour les infections des voies génitales basses que chez les femmes qui ne subissaient des tests que lorsqu'elles présentaient des symptômes d'infections des voies génitales basses.[71] Les femmes soumises à des tests de routine ont également donné naissance à moins de bébés présentant un faible poids à la naissance.. Even though these results look promising, the review was only based on one study so more research is needed into routine screening for low genital tract infections.[71]
Also periodontal disease has been shown repeatedly to be linked to preterm birth.[72][73] En revanche, infections virales, unless accompanied by a significant febrile response, are considered not to be a major factor in relation to preterm birth.[33]
Génétique
There is believed to be a maternal genetic component in preterm birth.[74] Estimated heritability of timing-of-birth in women was 34%. Cependant, the occurrence of preterm birth in families does not follow a clear inheritance pattern, thus supporting the idea that preterm birth is a non-Mendelian trait with a polygenic nature.[75]
Diagnostic
Placental alpha microglobulin-1
Placental alpha microglobulin-1 (PAMG-1) has been the subject of several investigations evaluating its ability to predict imminent spontaneous preterm birth in women with signs, symptômes, or complaints suggestive of preterm labor.[76][77][78][79][80][81] In one investigation comparing this test to fetal fibronectin testing and cervical length measurement via transvaginal ultrasound, the test for PAMG-1 (commercially known as the PartoSure test) has been reported to be the single best predictor of imminent spontaneous delivery within 7 days of a patient presenting with signs, symptômes, or complaints of preterm labor. Spécifiquement, the PPV, or positive predictive value, of the tests were 76%, 29%, et 30% for PAMG-1, fFN and CL, respectivement (P. < 0.01).[82]
Fibronectine fœtale
Fibronectine fœtale (fFN) has become an important biomarker—the presence of this glycoprotein in the cervical or vaginal secretions indicates that the border between the chorion and deciduas has been disrupted. Un test positif indique un risque accru d’accouchement prématuré, et un test négatif a une valeur prédictive élevée.[33] Il a été démontré que seulement 1% de femmes en cas de travail prématuré douteux accouchées dans la semaine suivante lorsque le test était négatif.[83]
Ultrason
Informations complémentaires: Incompétence cervicale
L'échographie obstétricale est devenue utile dans l'évaluation du col de l'utérus chez les femmes à risque d'accouchement prématuré. Un col court prématuré n’est pas souhaitable: Une longueur cervicale inférieure à 25 mm à ou avant 24 semaines d’âge gestationnel est la définition la plus courante de l’incompétence cervicale.[84]
Classification
Étapes du développement prénatal, avec les semaines et les mois numérotés depuis la dernière menstruation
Chez les humains, la définition habituelle d'une naissance prématurée est une naissance avant un âge gestationnel de 37 semaines complètes.[85] Chez le fœtus humain normal, several organ systems mature between 34 et 37 semaines, and the fetus reaches adequate maturity by the end of this period. One of the main organs greatly affected by premature birth is the lungs. The lungs are one of the last organs to mature in the womb; because of this, many premature babies spend the first days and weeks of their lives on ventilators. Donc, a significant overlap exists between preterm birth and prematurity. En général, preterm babies are premature and term babies are mature. Preterm babies born near 37 weeks often have no problems relating to prematurity if their lungs have developed adequate surfactant, which allows the lungs to remain expanded between breaths. Sequelae of prematurity can be reduced to a small extent by using drugs to accelerate maturation of the fetus, and to a greater extent by preventing preterm birth.
Prévention
Historically efforts have been primarily aimed to improve survival and health of preterm infants (tertiary intervention). Such efforts, cependant, have not reduced the incidence of preterm birth. Increasingly primary interventions that are directed at all women, and secondary intervention that reduce existing risks are looked upon as measures that need to be developed and implemented to prevent the health problems of premature infants and children.[86] Smoking bans are effective in decreasing preterm births.[87]
Before pregnancy
Adoption of specific professional policies can immediately reduce risk of preterm birth as the experience in assisted reproduction has shown when the number of embryos during embryo transfer was limited.[86] Many countries have established specific programs to protect pregnant women from hazardous or night-shift work and to provide them with time for prenatal visits and paid pregnancy-leave. The EUROPOP study showed that preterm birth is not related to type of employment, but to prolonged work (sur 42 hours per week) or prolonged standing (sur 6 heures par jour).[88] Aussi, night work has been linked to preterm birth.[89] Health policies that take these findings into account can be expected to reduce the rate of preterm birth.[86] Preconceptional intake of folic acid is recommended to reduce birth defects. There is significant evidence that long-term (> one year) use of folic acid supplement preconceptionally may reduce premature birth.[90][91][92] Reducing smoking is expected to benefit pregnant women and their offspring.[86]
During pregnancy
Une alimentation saine peut être instaurée à tout stade de la grossesse, y compris des ajustements nutritionnels, utilisation de suppléments vitaminiques, et l'arrêt du tabac.[86] La supplémentation en calcium chez les femmes ayant un faible apport alimentaire en calcium peut réduire le nombre de conséquences négatives, notamment l'accouchement prématuré., pré-éclampsie, et la mort maternelle.[93] L'Organisation Mondiale de la Santé (OMS) suggère 1,5 à 2 g de suppléments de calcium par jour, pour les femmes enceintes dont l'alimentation contient de faibles niveaux de calcium.[94] Il n’a pas été démontré qu’un apport supplémentaire en vitamines C et E réduit les taux de naissances prématurées.[95] Différentes stratégies sont utilisées dans l’administration des soins prénatals, et les études futures doivent déterminer si l'accent peut être mis sur le dépistage des femmes à haut risque, ou un soutien élargi aux femmes à faible risque, ou dans quelle mesure ces approches peuvent être fusionnées.[86] While periodontal infection has been linked with preterm birth, randomized trials have not shown that periodontal care during pregnancy reduces preterm birth rates.[86]
Additional support during pregnancy does not appear to prevent low birthweight or preterm birth.[96]
A review into using uterine monitoring at home to detect contractions and possible preterm births in women at higher risk of having a preterm baby found that it did not reduce the number of preterm births.[97] The research included in the review was poor quality but it showed that home monitoring may increase the number of unplanned antenatal visits and may reduce the number of babies admitted to special care when compared with women receiving normal antenatal care.[97]
Screening of low risk women
Screening for asymptomatic bacteriuria followed by appropriate treatment reduces pyelonephritis and reduces the risk of preterm birth.[98] Extensive studies have been carried out to determine if other forms of screening in low-risk women followed by appropriate intervention are beneficial, including screening for and treatment of Ureaplasma urealyticum, group B streptococcus, Trichomonas vaginalis, and bacterial vaginosis did not reduce the rate of preterm birth.[86] Routine ultrasound examination of the length of the cervix identifies patients at risk, but cerclage is not proven useful, and the application of a progestogen is under study.[86] Screening for the presence of fibronectin in vaginal secretions is not recommended at this time in women at low risk.
Self-care
Self-care methods to reduce the risk of preterm birth include proper nutrition, avoiding stress, seeking appropriate medical care, avoiding infections, and the control of preterm birth risk factors (par exemple. working long hours while standing on feet, carbon monoxide exposure, domestic abuse, et d'autres facteurs). Self-monitoring vaginal pH followed by yogurt treatment or clindamycin treatment if the pH was too high all seem to be effective at reducing the risk of preterm birth.[99][100]
Cervical assessment by ultrasound
There is tentative evidence that ultrasound measurement of the length of the cervix in those with preterm labor can help adjust management and results in the extension of pregnancy by about 4 jours.[101]
Reducing existing risks
Women are identified to be at increased risk for preterm birth on the basis of their past obstetrical history or the presence of known risk factors. Preconception intervention can be helpful in selected patients in a number of ways. Patients with certain uterine anomalies may have a surgical correction (i.e. removal of a uterine septum), and those with certain medical problems can be helped by optimizing medical therapies prior to conception, be it for asthma, diabète, hypertension, et d'autres.
Multiple pregnancies
In multiple pregnancies, which often result from use of assisted reproductive technology, there is a high risk of preterm birth. Selective reduction is used to reduce the number of fetuses to two or three.[102][103][104]
Reducing indicated preterm birth
A number of agents have been studied for the secondary prevention of indicated preterm birth. Trials using low-dose aspirin, fish oil, vitamin C and E, and calcium to reduce preeclampsia demonstrated some reduction in preterm birth only when low-dose aspirin was used.[86] Even if agents such as calcium or antioxidants were able to reduce preeclampsia, a resulting decrease in preterm birth was not observed.[86]
Reducing spontaneous preterm birth
Reduction in activity by the mother—pelvic rest, limited work, bed rest—may be recommended although there is no evidence it is useful with some concerns it is harmful.[105] Increasing medical care by more frequent visits and more education has not been shown to reduce preterm birth rates.[96] Use of nutritional supplements such as omega-3 polyunsaturated fatty acids is based on the observation that populations who have a high intake of such agents are at low risk for preterm birth, presumably as these agents inhibit production of proinflammatory cytokines. A randomized trial showed a significant decline in preterm birth rates,[106] and further studies are in the making.
Antibiotiques
While antibiotics can get rid of bacterial vaginosis in pregnancy, this does not appear to change the risk of preterm birth.[107] It has been suggested that chronic chorioamnionitis is not sufficiently treated by antibiotics alone (and therefore they cannot ameliorate the need for preterm delivery in this condition).[86]
Progestatifs
Progestogens—often given in the form of vaginal[108] progesterone or hydroxyprogesterone caproate—relax the uterine musculature, maintain cervical length, and possess anti-inflammatory properties; all of which invoke physiological and anatomical changes considered to be beneficial in reducing preterm birth. Two meta-analyses demonstrated a reduction in the risk of preterm birth in women with recurrent preterm birth by 40–55%.[109][110]
Progestogen supplementation also reduces the frequency of preterm birth in pregnancies where there is a short cervix.[111] A short cervix is one that is less than 25mm, as detected during a transvaginal cervical length assessment in the midtrimester.[112] Cependant, progestogens are not effective in all populations, as a study involving twin gestations failed to see any benefit.[113] Despite extensive research related to progestogen effectiveness, uncertainties remain concerning types of progesterone and routes of administration.[114]
Cervical cerclage
In preparation for childbirth, the woman’s cervix shortens. Preterm cervical shortening is linked to preterm birth and can be detected by ultrasonography. Cervical cerclage is a surgical intervention that places a suture around the cervix to prevent its shortening and widening. Numerous studies have been performed to assess the value of cervical cerclage and the procedure appears helpful primarily for women with a short cervix and a history of preterm birth.[111][115] Instead of a prophylactic cerclage, women at risk can be monitored during pregnancy by sonography, and when shortening of the cervix is observed, the cerclage can be performed.[86]
Gestion (Traitement)
Preterm birth at 32 semaines et 4 days with a weight of 2,000 g attached to medical equipment
Tertiary interventions are aimed at women who are about to go into preterm labor, or rupture the membranes or bleed preterm. The use of the fibronectin test and ultrasonography improves the diagnostic accuracy and reduces false-positive diagnosis. While treatments to arrest early labor where there is progressive cervical dilatation and effacement will not be effective to gain sufficient time to allow the fetus to grow and mature further, it may defer delivery sufficiently to allow the mother to be brought to a specialized center that is equipped and staffed to handle preterm deliveries.[116] In a hospital setting women are hydrated via intravenous infusion (as dehydration can lead to premature uterine contractions).[117]
If a baby has cardiac arrest at birth and is before 23 weeks or less than 400 g attempts at resuscitation are not indicated.[118]
Steroids
Severely premature infants may have underdeveloped lungs because they are not yet producing their own surfactant. This can lead directly to respiratory distress syndrome, also called hyaline membrane disease, in the neonate. To try to reduce the risk of this outcome, pregnant mothers with threatened premature delivery prior to 34 weeks are often administered at least one course of glucocorticoids, a steroid that crosses the placental barrier and stimulates the production of surfactant in the lungs of the baby.[15] Steroid use up to 37 weeks is also recommended by the American Congress of Obstetricians and Gynecologists.[15] Typical glucocorticoids that would be administered in this context are betamethasone or dexamethasone, often when the pregnancy has reached viability at 23 semaines.
In cases where premature birth is imminent, a second “rescue” course of steroids may be administered 12 à 24 hours before the anticipated birth. There are still some concerns about the efficacy and side effects of a second course of steroids, but the consequences of RDS are so severe that a second course is often viewed as worth the risk. UN 2015 Cochrane review supports the use of repeat dose(s) of prenatal corticosteroids for women still at risk of preterm birth seven days or more after an initial course.[119]
A Cochrane review from 2020 recommends the use of a single course of antenatal corticosteroids to accelerate fetal lung maturation in women at risk of preterm birth. Treatment with antenatal corticosteroids reduces the risk of perinatal death, neonatal death and respiratory distress syndrome and probably reduces the risk of IVH.[120]
Concerns about adverse effects of prenatal corticosteroids include increased risk for maternal infection, difficulty with diabetic control, and possible long-term effects on neurodevelopmental outcomes for the infants. There is ongoing discussion about when steroids should be given (i.e. only antenatally or postnatally too) et pour combien de temps (i.e. single course or repeated administration). Despite these unknowns, there is a consensus that the benefits of a single course of prenatal glucocorticosteroids vastly outweigh the potential risks.[121][122][123]
Antibiotiques
The routine administration of antibiotics to all women with threatened preterm labor reduces the risk of the baby to get infected with group B streptococcus and has been shown to reduce related mortality rates.[124]
When membranes rupture prematurely, obstetrical management looks for development of labor and signs of infection. Prophylactic antibiotic administration has been shown to prolong pregnancy and reduced neonatal morbidity with rupture of membranes at less than 34 semaines.[125] Because of concern about necrotizing enterocolitis, amoxicillin or erythromycin has been recommended, but not amoxicillin + clavulanic acid (co-amoxiclav).[125]
Tocolysis
A number of medications may be useful to delay delivery including: médicaments anti-inflammatoires non stéroïdiens, bloqueurs des canaux calciques, beta mimetics, and atosiban.[126] Tocolysis rarely delays delivery beyond 24–48 hours.[127] This delay, cependant, may be sufficient to allow the pregnant woman to be transferred to a center specialized for management of preterm deliveries and give administered corticosteroids to reduce neonatal organ immaturity. Meta-analyses indicate that calcium-channel blockers and an oxytocin antagonist can delay delivery by 2–7 days, and β2-agonist drugs delay by 48 hours but carry more side effects.[86][128] Magnesium sulfate does not appear to be useful to prevent preterm birth.[129] Its use before delivery, cependant, does appear to decrease the risk of cerebral palsy.[130]
Mode of delivery
The routine use of caesarean section for early delivery of infants expected to have very low birth weight is controversial,[131] and a decision concerning the route and time of delivery probably needs to be made on a case-by-case basis.
Neonatal care
Incubator for preterm baby
In developed countries premature infants are usually cared for in an NICU. The physicians who specialize in the care of very sick or premature babies are known as neonatologists. In the NICU, premature babies are kept under radiant warmers or in incubators (also called isolettes), which are bassinets enclosed in plastic with climate control equipment designed to keep them warm and limit their exposure to germs. Modern neonatal intensive care involves sophisticated measurement of temperature, respiration, fonction cardiaque, oxygénation, and brain activity. After delivery, plastic wraps or warm mattresses are useful to keep the infant warm on their way to the neonatal intensive care unit (USIN).[132] Treatments may include fluids and nutrition through intravenous catheters, oxygen supplementation, mechanical ventilation support, and medications.[133] In developing countries where advanced equipment and even electricity may not be available or reliable, simple measures such as kangaroo care (skin to skin warming), encouraging breastfeeding, and basic infection control measures can significantly reduce preterm morbidity and mortality. Bili lights may also be used to treat newborn jaundice (hyperbilirubinemia).
Water can be carefully provided to prevent dehydration but no so much to increase risks of side effects.[134]
Breathing support
In terms of respiratory support, there may be little or no difference in the risk of death or chronic lung disease between high flow nasal cannulae (HFNC) and continuous positive airway pressure (CPAP) or nasal intermittent positive pressure ventilation (NPPV).[135] For extremely preterm babies (born before 28 semaines’ gestation), targeting a higher versus a lower oxygen saturation range makes little or no difference overall to the risk of death or major disability.[136] Babies born before 32 weeks probably have a lower risk of death from bronchopulmonary dysplasia if they have CPAP immediately after being born, compared to receiving either supportive care or assisted ventilation.[137]
There is insufficient evidence for or against placing preterm stable twins in the same cot or incubator (co-bedding).[138]
Nutrition
Meeting the appropriate nutritional needs of preterm infants is important for long-term health. Optimal care may require a balance of meeting nutritional needs and preventing complications related to feeding. The ideal growth rate is not known, cependant, preterm infants usually require a higher energy intake compared to babies who are born at term.[139] The recommended amount of milk is often prescribed based on approximated nutritional requirements of a similar aged fetus who is not compromised.[140] An immature gastrointestinal tract (GI tract), conditions médicales (or co-morbidities), risk of aspirating milk, and necrotizing enterocolitis may lead to difficulties in meeting this high nutritional demand and many preterm infants have nutritional deficits that may result in growth restrictions.[140] En outre, very small preterm infants cannot coordinate sucking, avaler, and breathing.[141] Tolerating a full enteral feeding (the prescribed volume of milk or formula) is a priority in neonatal care as this reduces the risks associated with venous catheters including infection, and may reduce the length of time the infant requires specialized care in the hospital.[140] Different strategies can be used to optimize feeding for preterm infants. The type of milk/formula and fortifiers, voie d'administration (by mouth, tube feeding, venous catheter), timing of feeding, quantity of milk, continuous or intermittent feeding, and managing gastric residuals are all considered by the neonatal care team when optimizing care. The evidence in the form of high quality randomized trials is generally fairly weak in this area, and for this reason different neonatal intensive care units may have different practices and this results in a fairly large variation in practice. The care of preterm infants also varies in different countries and depends on resources that are available.[140]
Human breast milk and formula
The American Academy of Pediatrics recommended feeding preterm infants human milk, finding “significant short- and long-term beneficial effects,” including lower rates of necrotizing enterocolitis (NEC).[142] In the absence of evidence from randomised controlled trials about the effects of feeding preterm infants with formula compared with mother’s own breast milk, data collected from other types of studies suggest that mother’s own breast milk is likely to have advantages over formula in terms of the baby’s growth and development.[143][139] When a mother’s breast milk is not available, formula is probably better than donor breast milk for preterm babies in terms of weight gain, linear growth and head growth but there may be little or no difference in terms of neuro-developmental disability, death or necrotising enterocolitis.[144]
Fortified human breast milk and preterm/term formula
Breast milk or formula alone may not be sufficient to meet the nutritional needs of some preterm infants. Fortification of breast milk or formula by adding extra nutrients is an approach often taken for feeding preterm infants, with the goal of meeting the high nutritional demand.[139] High quality randomized controlled trials are needed in this field to determine the effectiveness of fortification.[145] It is unclear if fortification of breast milk improves outcomes in preterm babies, though it may speed growth.[145] Supplementing human milk with extra protein may increase short-term growth but the longer-term effects on body composition, growth and brain development are uncertain.[146][147] Higher protein formula (entre 3 et 4 grams of protein per kilo of body weight) may be more effective than low protein formula (less than 3 grams per kilo per day) for weight gain in formula-fed low-birth-weight infants.[148] There is insufficient evidence about the effect on preterm babies’ growth of supplementing human milk with carbohydrate,[149] graisse,[150][151] and branched-chain amino acids.[152] Inversement, there is some indication that preterm babies who cannot breastfeed may do better if they are fed only with diluted formula compared to full strength formula but the clinical trial evidence remains uncertain.[153]
Individualizing the nutrients and quantities used to fortify enteral milk feeds in infants born with very low birth weight may lead to better short-term weight gain and growth but the evidence is uncertain for longer term outcomes and for the risk of serious illness and death.[154] This includes targeted fortification (adjusting the level of nutrients in response to the results of a test on the breast milk) and adjustable fortification (adding nutrients based on testing the infant).[154]
Multi-nutrient fortifier used to fortify human milk and formula has traditionally been derived from bovine milk.[155] Fortifier derived from humans is available, cependant, the evidence from clinical trials is uncertain and it is not clear if there are any differences between human-derived fortifier and bovine-derived fortifier in terms of neonatal weight gain, feeding intolerance, infections, or the risk of death.[155]
Timing of feeds
For very preterm infants, most neonatal care centres start milk feeds gradually, rather than starting with a full enteral feeding right away, cependant, is not clear if starting full enteral feeding early effects the risk of necrotising enterocolitis.[140] Dans ces cas, the preterm infant would be receiving the majority of their nutrition and fluids intravenously. The milk volume is usually gradually increased over the following weeks.[140] Research into the ideal timing of enteral feeding and whether delaying enteral feeding or gradually introducing enteral feeds is beneficial at improving growth for preterm infants or low birth weight infants is needed.[140] En outre, the ideal timing of enteral feeds to prevent side effects such as necrotising enterocolitis or mortality in preterm infants who require a packed red blood cell transfusion is not clear.[156] Potential disadvantages of a more gradual approach to feeding preterm infants associated with less milk in the gut and include slower GI tract secretion of hormones and gut motility and slower microbial colonization of the gut.[140]
Regarding the timing of starting fortified milk, preterm infants are often started on fortified milk/formula once they are fed 100 mL/kg of their body weight. Other some neonatal specialists feel that starting to feed a preterm infant fortified milk earlier is beneficial to improve intake of nutrients.[157] The risks of feeding intolerance and necrotising enterocolitis related to early versus later fortification of human milk are not clear.[157] Once the infant is able to go home from the hospital there is limited evidence to support prescribing a preterm (fortified) formula.[158]
Intermittent feeding versus continuous feeding
For infants who weigh less than 1500 grammes, tube feeding is usually necessary.[141] Most often, neonatal specialists feed preterm babies intermittently with a prescribed amount of milk over a short period of time. Par exemple, a feed could last 10-20 minutes and be given every 3 heures. This intermittent approach is meant to mimic conditions of normal bodily functions involved with feeding and allow for a cyclic pattern in the release of gastrointestinal tract hormones to promote development of the gastrointestinal system.[141] Dans certains cas, continuous nasogastric feeding is sometimes preferred. There is low to very low certainty evidence to suggest that low birth weight babies who receive continuous nasogastic feeding may reach the benchmark of tolerating full enteral feeding later than babies fed intermittently and it is not clear if continuous feeding has any effect on weight gain or the number of interruptions in feedings.[141] Continuous feeding may have little to no effect on length of body growth or head circumference and the effects of continuous feeding on the risk of developing necrotising enterocolitis is not clear.[141]
High volume feeds
High-volume (plus que 180 mL per Kg per day) enteral feeds of fortified or non-fortified human breast milk or formula may improve weight gain while the pre-term infant is hospitalized, cependant, there is insufficient evidence to determine if this approach improves growth of the neonate and other clinical outcomes including length of hospital stay.[139] The risks or adverse effects associated with high-volume enteral feeding of preterm infants including aspiration pneumonia, reflux, apnoea, and sudden oxygen desaturation episodes have not been reported in the trials considered in a 2021 systematic review.[139]
Parenteral (intraveneous) nutrition
For preterm infants who are born after 34 semaines de gestation (“late preterm infants”) who are critically ill and cannot tolerate milk, there is some weak evidence that the infant may benefit from including amino acids and fats in the intravenous nutrition at a later time point (72 hours or longer from hospital admission) versus early (less than 72 hours from admission to hospital), however further research is required to understand the ideal timing of starting intravenous nutrition.[159]
Gastric residuals
For preterm infants in neonatal intensive care on gavage feeds, monitoring the volume and colour of gastric residuals, the milk and gastrointestinal secretions that remain in the stomach after a set amount of time, is common standard of care practice.[160] Gastric residual often contains gastric acid, hormones, enzymes, and other substances that may help improve digestion and mobility of the gastrointestinal tract. Analysis of gastric residuals may help guide timing of feeds.[160] Increased gastric residual may indicate feeding intolerance or it may be an early sign of necrotizing enterocolitis. Increased gastric residual may be caused by an underdeveloped gastrointestinal system that leads to slower gastric emptying or movement of the milk in the intestinal tract, reduced hormone or enzyme secretions from the gastrointestinal tract, duodenogastric reflux, formula, médicaments, and/or illness.[160] The clinical decision to discard the gastric residuals (versus re-feeding) is often individualized based on the quantity and quality of the residual.[160] Some experts also suggest replacing the fresh milk or curded milk and bile-stained aspirates, but not replacing haemorrhagic residual.[160] Evidence to support or refute the practice of re-feeding preterm infants with gastric residuals is lacking.[160]
Hearing assessment
The Joint Committee on Infant Hearing (JCIH) state that for preterm infants who are in the neonatal intensive care unit (USIN) for a prolonged time should have a diagnostic audiologic evaluation before they are discharged from the hospital.[161] Well babies follow a 1-2-3-month benchmark timeline where they are screened, diagnosed, and receiving intervention for a hearing loss. Cependant, very premature babies it might not be possible to complete a hearing screen at one month of age due to several factors. Once the baby is stable an audiologic evaluation should be performed. For premature babies in the NICU, auditory brainstem response (ABR) testing is recommended. If the infant doesn’t pass the screen, they should be referred for an audiologic evaluation by an audiologist.[161] If the infant is on aminoglycosides such as gentamicin for less than five days they should be monitored and have a follow up 6–7 months of being discharged from the hospital to ensure there is no late onset hearing loss due to the medication.[161]
Outcomes and prognosis
Preterm infants survival rates[162][163][164][165][166][167]
Preterm births can result in a range of problems including mortality and physical and mental delays.[168][169]
Mortality and morbidity
In the U.S. where many neonatal infections and other causes of neonatal death have been markedly reduced, prematurity is the leading cause of neonatal mortality at 25%.[170] Prematurely born infants are also at greater risk for having subsequent serious chronic health problems as discussed below.
The earliest gestational age at which the infant has at least a 50% chance of survival is referred to as the limit of viability. As NICU care has improved over the last 40 années, the limit of viability has reduced to approximately 24 semaines.[171][172] Most newborns who die, et 40% of older infants who die, were born between 20 et 25.9 semaines (âge gestationnel), during the second trimester.[20]
As risk of brain damage and developmental delay is significant at that threshold even if the infant survives, there are ethical controversies over the aggressiveness of the care rendered to such infants. The limit of viability has also become a factor in the abortion debate.[173]
Specific risks for the preterm neonate
Preterm infants usually show physical signs of prematurity in reverse proportion to the gestational age. Par conséquent, they are at risk for numerous medical problems affecting different organ systems.
Neurological problems include apnea of prematurity, hypoxic-ischemic encephalopathy (HIE), retinopathy of prematurity (ROP),[174] developmental disability, transient hyperammonemia of the newborn, cerebral palsy and intraventricular hemorrhage, the latter affecting 25% of babies born preterm, usually before 32 weeks of pregnancy.[175] Mild brain bleeds usually leave no or few lasting complications, but severe bleeds often result in brain damage or even death.[175] Neurodevelopmental problems have been linked to lack of maternal thyroid hormones, at a time when their own thyroid is unable to meet postnatal needs.[176]
Cardiovascular complications may arise from the failure of the ductus arteriosus to close after birth: patent ductus arteriosus (PDA).
Respiratory problems are common, specifically the respiratory distress syndrome (RDS or IRDS) (previously called hyaline membrane disease). Another problem can be chronic lung disease (previously called bronchopulmonary dysplasia or BPD).
Gastrointestinal and metabolic issues can arise from neonatal hypoglycemia, feeding difficulties, rickets of prematurity, hypocalcemia, inguinal hernia, and necrotizing enterocolitis (NEC).
Hematologic complications include anemia of prematurity, thrombocytopénie, and hyperbilirubinemia (jaunisse) that can lead to kernicterus.
Infection, including sepsis, pneumonie, and urinary tract infection [1]
Une étude de 241 children born between 22 et 25 weeks who were currently of school age found that 46 percent had severe or moderate disabilities such as cerebral palsy, vision or hearing loss and learning problems. Thirty-four percent were mildly disabled and 20 percent had no disabilities, alors que 12 percent had disabling cerebral palsy.[177][178] Jusqu'à 15 de 100 premature infants have significant hearing loss.[179]
Survie
La chance de survie à 22 les semaines, c'est environ 6%, alors qu'à 23 semaines c'est 26%, 24 semaines 55% et 25 semaines environ 72% à compter de 2016.[22] With extensive treatment up to 30% of those who survive birth at 22 weeks survive longer term as of 2019.[180] The chances of survival without long-term difficulties is less.[23] Of those who survive following birth at 22 semaines 33% have severe disabilities.[180] In the developed world overall survival is about 90% while in low-income countries survival rates are about 10%.[181]
Some children will adjust well during childhood and adolescence,[168] although disability is more likely nearer the limits of viability. A large study followed children born between 22 et 25 weeks until the age of 6 ans. Of these children, 46 percent had moderate to severe disabilities such as cerebral palsy, vision or hearing loss and learning disabilities, 34 percent had mild disabilities, et 20 percent had no disabilities. Twelve percent had disabling cerebral palsy.[178]
As survival has improved, the focus of interventions directed at the newborn has shifted to reduce long-term disabilities, particularly those related to brain injury.[168] Some of the complications related to prematurity may not be apparent until years after the birth. A long-term study demonstrated that the risks of medical and social disabilities extend into adulthood and are higher with decreasing gestational age at birth and include cerebral palsy, intellectual disability, disorders of psychological development, comportement, and emotion, disabilities of vision and hearing, and epilepsy.[182] Standard intelligence tests showed that 41 percent of children born between 22 et 25 weeks had moderate or severe learning disabilities when compared to the test scores of a group of similar classmates who were born at full term.[178] It is also shown that higher levels of education were less likely to be obtained with decreasing gestational age at birth.[182] People born prematurely may be more susceptible to developing depression as teenagers.[183] Some of these problems can be described as being within the executive domain and have been speculated to arise due to decreased myelinization of the frontal lobes.[184] Studies of people born premature and investigated later with MRI brain imaging, demonstrate qualitative anomalies of brain structure and grey matter deficits within temporal lobe structures and the cerebellum that persist into adolescence.[185] Throughout life they are more likely to require services provided by physical therapists, occupational therapists, or speech therapists.[168]
Despite the neurosensory, mental and educational problems studied in school age and adolescent children born extremely preterm, the majority of preterm survivors born during the early years of neonatal intensive care are found to do well and to live fairly normal lives in young adulthood.[186] Young adults born preterm seem to acknowledge that they have more health problems than their peers, yet feel the same degree of satisfaction with their quality of life.[187]
Beyond the neurodevelopmental consequences of prematurity, infants born preterm have a greater risk for many other health problems. Par exemple, children born prematurely have an increased risk for developing chronic kidney disease.[188]
Épidémiologie
Disability-adjusted life year for prematurity and low birth weight per 100,000 inhabitants in 2004.[189]
aucune donnée
less than 120
120-240
240-360
360-480
480-600
600-720
720-840
840-960
960-1080
1080-1200
1200-1500
plus que 1500
Preterm birth complicates the births of infants worldwide affecting 5% à 18% of births.[67] In Europe and many developed countries the preterm birth rate is generally 5–9%, and in the U.S. it has even risen to 12–13% in the last decades.[190]
As weight is easier to determine than gestational age, the World Health Organization tracks rates of low birth weight (< 2,500 grammes), which occurred in 16.5 percent of births in less developed regions in 2000.[191] It is estimated that one third of these low birth weight deliveries are due to preterm delivery. Weight generally correlates to gestational age; cependant, infants may be underweight for other reasons than a preterm delivery. Neonates of low birth weight (LBW) have a birth weight of less than 2,500 g (5 lb 8 oz) and are mostly but not exclusively preterm babies as they also include small for gestational age (SGA) babies. Weight-based classification further recognizes Very Low Birth Weight (VLBW) which is less than 1,500 g, and Extremely Low Birth Weight (ELBW) which is less than 1,000 g.[192] Almost all neonates in these latter two groups are born preterm.
À propos 75% of nearly a million deaths due to preterm deliver would survive if provided warmth, breastfeeding, treatments for infection, and breathing support.[181] Les complications liées aux naissances prématurées ont entraîné 740,000 deaths in 2013, vers le bas de 1.57 millions en 1990.[21]
Society and culture
Economics
Preterm birth is a significant cost factor in healthcare, not even considering the expenses of long-term care for individuals with disabilities due to preterm birth. UN 2003 study in the U.S. determined neonatal costs to be $224,400 for a newborn at 500–700 g versus $1,000 at over 3,000 g. The costs increase exponentially with decreasing gestational age and weight.[193] Le 2007 Institute of Medicine report Preterm Birth[194] found that the 550,000 premature babies born each year in the U.S. run up about $26 billion in annual costs, mostly related to care in neonatal intensive care units, but the real tab may top $50 billion.[195]
Notable cases
James Elgin Gill (born on 20 Peut 1987 in Ottawa, Ontario, Canada) was the earliest premature baby in the world, until that record was broken in 2004. He was 128 days premature (21 semaines et 5 jours’ gestation) and weighed 1 pound 6 ounces (624 g). He survived.[196][197]
Dans 2014, Lyla Stensrud, born in San Antonio, Texas, NOUS. became the youngest premature baby in the world. She was born at 21 semaines 4 days and weighed 410 grammes (less than a pound). Kaashif Ahmad resuscitated the baby after she was born. As of November 2018, Lyla was attending preschool. She had a slight delay in speech, but no other known medical issues or disabilities.[198]
Amillia Taylor is also often cited as the most premature baby.[199] She was born on 24 Octobre 2006 in Miami, Floride, NOUS. à 21 semaines et 6 jours’ gestation.[200] This report has created some confusion as her gestation was measured from the date of conception (through in vitro fertilization) rather than the date of her mother’s last menstrual period, making her appear 2 weeks younger than if gestation was calculated by the more common method.[183] At birth, she was 9 inches (22.9 cm) long and weighed 10 ounces (280 g).[199] She suffered digestive and respiratory problems, together with a brain hemorrhage. She was discharged from the Baptist Children’s Hospital on 20 Février 2007.[199]
The record for the smallest premature baby to survive was held for a considerable amount of time by Madeline Mann, who was born in 1989 à 26 semaines, weighing 9.9 ounces (280 g) and measuring 9.5 inches (241.3 mm) long.[201] This record was broken in September 2004 by Rumaisa Rahman, who was born in the same hospital, Loyola University Medical Center in Maywood, Illinois.[202] à 25 semaines’ gestation. At birth, she was 8 inches (200 mm) long and weighed 261 grammes (9.2 oz).[203] Her twin sister was also a small baby, weighing 563 grammes (1 lb 3.9 oz) à la naissance. During pregnancy their mother had pre-eclampsia, requiring birth by caesarean section. The larger twin left the hospital at the end of December, while the smaller remained there until 10 Février 2005 by which time her weight had increased to 1.18 kilos (2.6 lb).[204] Generally healthy, the twins had to undergo laser eye surgery to correct vision problems, a common occurrence among premature babies.
In May 2019, Sharp Mary Birch Hospital for Women & Newborns in San Diego announced that a baby nicknamed “Saybie” had been discharged almost five months after being born at 23 semaines’ gestation and weighing 244 grammes (8.6 oz). Saybie was confirmed by Dr. Edward Bell of the University of Iowa, which keeps the Tiniest Babies Registry, to be the new smallest surviving premature baby in that registry.[205]
The world’s smallest premature boy to survive was born in February 2009 at Children’s Hospitals and Clinics of Minnesota in Minneapolis, Minnesota, NOUS. Jonathon Whitehill was born at 25 semaines’ gestation with a weight of 310 grammes (11 oz). He was hospitalized in a neonatal intensive care unit for five months, and then discharged.[206]
Dans 2020, at the height of the novel Coronavirus pandemic, the worlds most premature baby was born.[207] The baby, named Richard Hutchinson, was born at Children’s Hospitals and Clinics of Minnesota in Minneapolis, Minnesota, NOUS. on June 5, 2020, à 21 semaines 2 days gestation. At birth he weighed a remarkable twelve ounces. He remained hospitalized until November 2020, which he was then discharged.[208]
Historical figures who were born prematurely include Johannes Kepler (né en 1571 at seven months’ gestation), Isaac Newton (né en 1642, small enough to fit into a quart mug, according to his mother), Winston Churchill (né en 1874 at seven months’ gestation), and Anna Pavlova (né en 1885 at seven months’ gestation).[209]
Effect of the coronavirus pandemic
During the COVID-19 pandemic, a drastic drop in the rate of premature births has been reported in many countries, ranging from a 20% reduction to a 90% drop in the starkest cases. Studies in Ireland and Denmark first noticed the phenomenon, and it has been confirmed elsewhere. There is no universally accepted explanation for this drop as of August 2020. Hypotheses include additional rest and support for expectant mothers staying at home, less air pollution due to shutdowns and reduced car fumes, and reduced likelihood of catching other diseases and viruses in general due to the lockdowns.[210]

Examen de cas scientifiques
Souhaitez-vous savoir si les programmes cliniques actuels, développements récents en recherche, ou des approches émergentes peuvent être adapté à votre situation individuelle?
Envoyez votre question à notre équipe scientifique. Le siège social de NBScience au Royaume-Uni coordonne les demandes de renseignements à travers le réseau international de centres médicaux, scientifiques, et consultants spécialisés.
- Examen des informations que vous fournissez
- Informations pertinentes sur la recherche et les programmes cliniques
- Une réponse claire et adaptée à votre situation
Aucune obligation. Votre question sera examinée de manière confidentielle.
Informations pédagogiques et de recherche uniquement. Ce service ne constituer un avis médical, diagnostic, ordonnance, ou un personnalisé recommandation de traitement.

